Chronic lymphocytic leukemia (CLL) is shaped by your biology, down to the chromosomal level, which determines how your disease behaves and which treatments will work best for you.
Researchers and oncologists now recognize CLL as a condition shaped by distinct genetic profiles, which means your care team needs precise information before building your personalized care plan. That information comes from biomarkers, measurable biological indicators that reveal how aggressively your disease is likely to progress and how it may respond to therapy.
Three tests sit at the center of this picture. The FISH test for CLL, IGHV mutational status, and TP53 mutation and deletion analysis. Together, they give your care team a genomic map of your disease, one that guides decisions about prognosis, treatment timing, and the right therapy for your specific situation. Research supports that patients who receive comprehensive genetic marker testing experience better outcomes than those who don’t.
Critically, these tests aren’t a one-time event. Because CLL can evolve over time, repeating them before every new line of therapy ensures your care team is always working from an accurate, current picture of your disease. Starting with FISH testing is where that genomic profile begins to take shape.
FISH testing: identifying chromosomal deletions and risk patterns
Fluorescence In Situ Hybridization (FISH) testing maps specific chromosomal abnormalities in your CLL cells, giving your care team a clearer picture of how your disease is likely to behave.
The test works by tagging targeted DNA sequences with fluorescent dyes, then using a microscope to detect deletions, duplications, or rearrangements at precise chromosomal locations. Unlike standard cytogenetics, FISH is a blood test that examines the chromosomes inside cancerous lymphocytes to look for changes and help determine how quickly your CLL may progress.
Risk stratification from FISH follows a recognized hierarchy:
- 13q deletion (del 13q), The most common finding in CLL and, when present as the sole abnormality, carries a favorable prognosis with slower disease progression.
- Trisomy 12, Trisomy 12 is one of the four common chromosomal alterations found in chronic lymphocytic leukemia and is associated with an intermediate prognosis.
- 11q deletion (del 11q), Linked to bulky lymph node disease and more aggressive progression, representing a high-risk profile.
- 17p deletion (del 17p), The highest-risk finding detected by FISH, reflecting loss of the TP53 tumor suppressor region and resistance to certain therapies.
Understanding where your results fall on this spectrum is foundational, and it connects directly to another critical marker, IGHV mutational status, which provides its own distinct layer of prognostic information.
IGHV mutation status. A timeline for disease progression
The IGHV (immunoglobulin heavy chain variable region) gene encodes part of the antibody structure produced by B cells. During normal B-cell development, these genes undergo a mutation process called somatic hypermutation, essentially a refinement that improves antibody function. CLL cells that carry this mutation are classified as mutated IGHV, while those that skipped this developmental step are classified as unmutated IGHV.
Patients with unmutated IGHV tend to have more aggressive disease, shorter time to first treatment, and fewer durable responses compared to those with mutated IGHV. Mutated status is generally associated with slower progression and a higher likelihood of achieving long-term remission, particularly with certain therapies.
What makes IGHV uniquely valuable is its stability. Unlike TP53 mutations or chromosomal deletions detected by FISH testing, IGHV status reflects how the CLL clone originally developed and typically doesn’t change over the course of the disease. Your care team can test it once and rely on that result as a consistent anchor in your personalized care plan.
Evidence-based guidance powered by NCCN Guidelines®
Personalized treatment plans shaped by the latest oncology standards—tailored to your diagnosis.
Get started
View your personalized treatment plan in the Outcomes4Me app
Use your diagnosis to unlock personalized NCCN Guidelines®-aligned recommendations.
Continue in app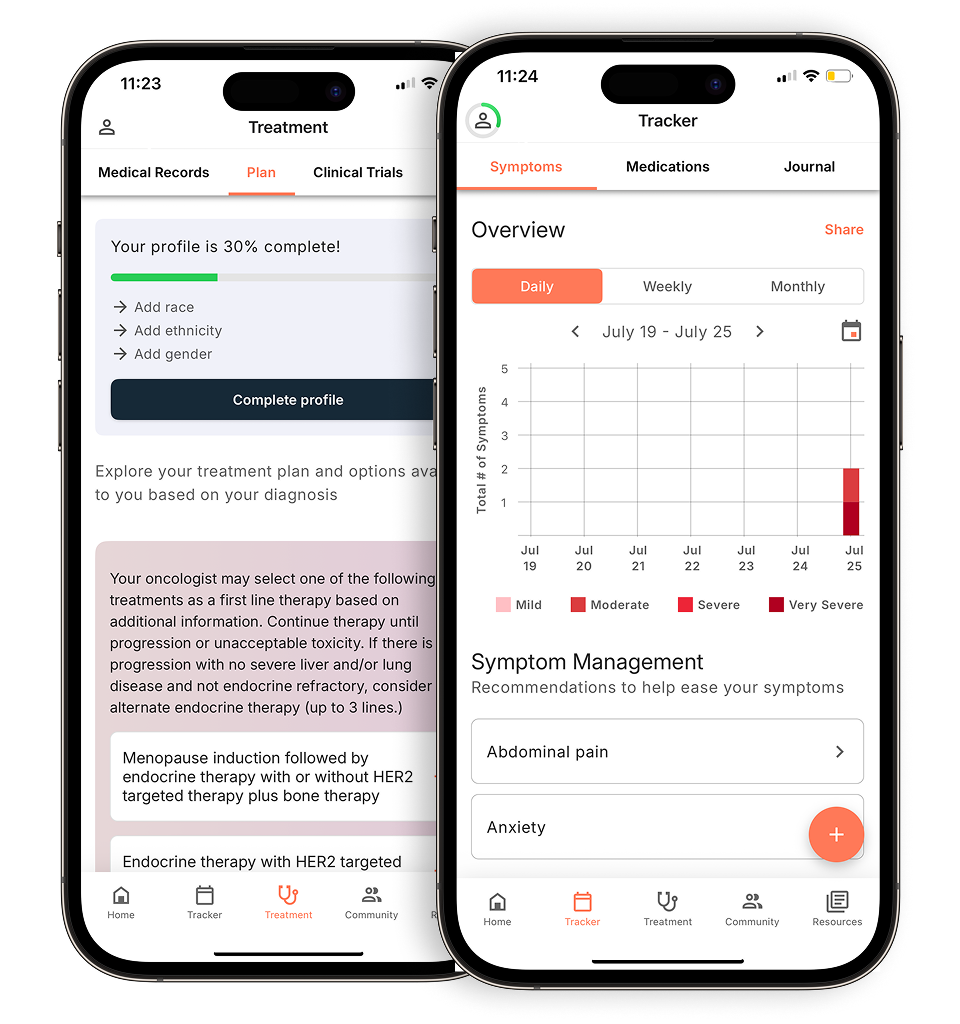
This stability shapes therapy decisions in meaningful ways. Patients with mutated IGHV have a more favorable prognosis and are typically considered for chemoimmunotherapy as a treatment option, though individual outcomes vary. Patients with unmutated IGHV tend to have shorter progression-free survival with traditional chemoimmunotherapy, though newer targeted therapies like acalabrutinib-venetoclax combinations may offer better outcomes. Understanding exactly how those decisions unfold is where the next piece of the picture comes into focus.
The strategic shift. How biomarkers dictate modern CLL treatment
Biomarker testing has changed how care teams approach CLL, moving treatment decisions toward precisely matched, genetics-informed therapies rather than standard chemotherapy protocols.
For years, fludarabine, cyclophosphamide, and rituximab (FCR) was the standard first-line approach. But FCR carries significant toxicity, and research shows that chemoimmunotherapy, including FCR, produces worse outcomes than targeted therapies in patients with high-risk genetic factors like unmutated IGHV or certain mutations. Patients with unmutated IGHV tend to respond better to newer targeted therapies like acalabrutinib-venetoclax combinations than to traditional chemotherapy, while those with unmutated IGHV often see early relapse despite initial response to FCR.
BTK inhibitors have become the preferred route for unmutated IGHV patients, offering sustained disease control without chemotherapy’s cumulative side effects. Your IGHV result helps narrow down which treatment path makes the most clinical sense.
TP53 status adds another layer. When TP53 mutations or 17p deletions are present, standard chemotherapy is largely ineffective, and BCL-2 inhibitors or targeted clinical trials become the evidence-based alternatives your care team will consider.
One increasingly important distinction shaping personalized care plans is treatment duration. Patients without high-risk genetics may qualify for fixed-duration regimens, a defined treatment course followed by a treatment-free period. Those with higher-risk profiles often require continuous therapy. This distinction matters for quality of life, and knowing your biomarker profile puts you in a stronger position to engage in shared decision-making with your care team about what that looks like in practice. The next section explores how specific mutations influence prognosis directly.
Understanding the prognosis for high-risk mutations
When TP53 mutations or 17p deletions are present, your care team needs to choose differently. Modern medicine has made that choice far more effective.
TP53 status is among the most consequential findings in a CLL workup. Historically, patients with these mutations faced limited options and poor outcomes with standard chemotherapy. That picture has shifted considerably. Novel targeted agents, particularly BTK inhibitors and BCL-2 inhibitors, have meaningfully improved progression-free survival (PFS) even for patients carrying high-risk markers like del(17p).
TP53 mutations or 17p deletions typically signal that chemotherapy-based approaches are unlikely to be effective and may cause more harm than benefit. Your care team will generally move toward a personalized care plan built around non-chemotherapy options instead.
And the outcomes data now supports that shift. In the era of novel agents, high-risk CLL groups that once had median PFS measured in months are achieving sustained responses lasting several years. That’s a fundamental change in what “high-risk” actually means in practice today. Understanding these prognostic markers is one piece of the picture, but CLL can also evolve over time, and knowing how to recognize those shifts matters just as much.
Managing transitions. Richter’s transformation and biomarker shifts
This shift changes both the urgency and the approach your care team takes. And it raises a question many patients ask. How long can you live with Richter’s transformation? Outcomes vary, but historically, survival with Richter’s transformation has been measured in months rather than years without aggressive intervention, which is why early recognition matters so much.
Certain biomarkers signal a higher risk of this transformation occurring:
Cancer care guidance for every step of your journey
Get treatment options, clinical trials, and support tailored to your diagnosis--all in one place.
Get started
See treatment options, manage symptoms, and stay informed—all in the app
View treatment options and trials personalized to your diagnosis—plus track progress in real time.
Continue in app- NOTCH1 mutations are among the most consistently associated with Richter’s risk
- Several chromosomal abnormalities, including del(17p), TP53 disruption, and trisomy 12, are associated with increased risk of Richter’s transformation in CLL patients
- Unmutated IGHV status and TP53 disruptions add additional layers of instability and risk for Richter’s transformation
If your CLL stops responding to treatment, repeat biomarker testing becomes essential. Your care team may order fresh FISH or TP53 sequencing because the genetic profile of CLL can shift over time, with clones that were once minor expanding under treatment pressure and dominating. Understanding exactly what’s driving resistance shapes what comes next. That connection between lab methodology and clinical interpretation is worth examining closely.
Behind the scenes. Why lab methodology matters for your results
The test result on your pathology report is only as reliable as the method used to generate it. Not every lab uses the same approach.
Two core technologies power CLL genetic testing. FISH is a cytogenetic technique that scans for known chromosomal deletions, like 17p deletion. FISH has a limitation: FISH testing detects specific chromosomal abnormalities associated with CLL, such as deletions on chromosomes 11, 13, and 17, as well as trisomy 12. Next-generation sequencing (NGS) is another important tool your care team may use. Genetic testing can detect TP53 mutations, which are an important factor in determining your CLL prognosis and treatment options.
Complex karyotyping adds another layer. CLL with multiple chromosomal abnormalities tends to be more aggressive and may show reduced response to standard therapies, particularly when abnormalities include del(17p) or TP53 mutations. Not all labs perform this analysis routinely.
This is why your care team should ideally work with a specialized hematopathology lab. Interpreting CLL genetics isn’t straightforward, subtle variants need expert review to distinguish clinically meaningful mutations from background noise.
When you receive a pathology report, look specifically for sections labeled “FISH panel,” “molecular studies,” or “karyotype.” IGHV mutational status and TP53 sequencing results typically appear under molecular studies. If those sections are absent, it’s worth asking your care team whether additional testing is warranted, because understanding what’s really driving your CLL often requires looking deeper than a standard panel reveals. And there’s more to this picture than labs alone, as the next section explores.
Industry insights. What most guides miss about CLL testing
CLL cells don’t stay static. They evolve, and a test result from five years ago may no longer reflect the disease your care team is treating today.
Clonal evolution is the process by which CLL cells acquire new genetic mutations over time. FISH findings, TP53 status, and other cytogenetic markers can shift as the disease progresses, meaning repeat testing before each new line of treatment is essential for building an accurate personalized care plan.
One practical approach many guides overlook is the timing of testing during the “watch and wait” period. Because CLL often progresses slowly, testing is sometimes deferred during the watch and wait period. This reflects a deliberate strategy, since the biomarker profile at the point of treatment is what matters most for selecting therapy.
And here’s where a common pitfall emerges. Patients and even some clinicians assume that all markers are subject to change. IGHV mutational status is an important part of your genetic testing after a CLL diagnosis and helps determine your prognosis and treatment options. Re-testing IGHV is generally unnecessary, unlike FISH or TP53 assessments, which should be revisited as disease evolves.
Understanding which markers are fixed and which can shift helps you ask sharper questions of your care team. That distinction also matters because genetic forecasting, even with the best testing, carries real limitations worth examining closely.
Limitations and considerations in genetic forecasting
Genetic biomarkers in CLL reveal probabilities, not certainties. Understanding that distinction can meaningfully change how you interpret your results.
Probabilities vs. predictions. While a high-risk FISH finding or unmutated IGHV status may reliably predict outcomes for groups of patients, these factors do not determine the outcome for any one individual, as every person’s CLL is slightly different. Your care team weighs these markers alongside your clinical symptoms, overall health, and treatment history. In practice, lab values alone rarely drive decisions. How you’re feeling and how your disease is behaving often carry equal weight.
Variant Allele Frequency (VAF). Not all mutations are created equal. Variant Allele Frequency (VAF) is a measure used in genetic testing that may reflect what proportion of cells in a sample carry a given mutation, though your care team can explain how this applies to your specific results. A TP53 mutation present in five percent of cells tells a different story than one found in sixty percent. Genetic changes in your CLL cells, such as deletions and mutations, can affect how aggressive the disease is likely to be and how well it may respond to treatment.
Psychological weight. Receiving a “high-risk” genetic report can trigger significant emotional challenges. A label on a pathology report doesn’t define your trajectory. Talking openly with your care team and seeking peer support helps you process that information constructively rather than in isolation.
Access gaps. Testing availability isn’t uniform. Geography, insurance coverage, and healthcare system resources all influence whether comprehensive genomic panels are offered. If you haven’t been tested, it’s worth asking your care team what options exist.
Knowing where to find credible, up-to-date genetic information is the logical next step, which is exactly where reliable sources become essential.
Where to look next. Finding credible genetic information
Knowing where to find trustworthy information about CLL genetics is just as important as understanding what the tests actually measure.
With so much conflicting content online, narrowing your sources to a short, reliable list makes a real difference. Peer-reviewed journals, such as those indexed on PubMed or ScienceDirect, publish the clinical trial data your care team uses to make treatment decisions. They’re dense, but even scanning an abstract can confirm whether a claim you’ve read elsewhere holds up scientifically.
Clinical practice guidelines from national oncology networks, such as NCCN, translate that research into standardized care recommendations. And patient advocacy organizations, including the CLL Society, do the valuable work of converting complex genomic data into language that’s genuinely accessible without losing clinical accuracy.
Academic medical centers are worth considering if your results raise questions your local team can’t fully address. A second opinion from a specialist at a major research institution, particularly one with a dedicated hematologic oncology program, can clarify ambiguous FISH findings or borderline IGHV results. That’s a reasonable step when the stakes are high.
Key takeaways: the bottom line on CLL testing
FISH, IGHV, and TP53 form the “big three” of CLL testing, and understanding what they reveal is the foundation of any informed personalized care plan.
These markers work together to tell your care team whether targeted therapy or traditional chemotherapy is the right path forward. Critically, testing needs to happen at diagnosis and again before every new treatment line, because genetic profiles can shift as the disease evolves.
A few key reminders to carry forward:
- High-risk doesn’t mean no options. It means a specific strategy is required, often one that bypasses the pathways a mutation has disrupted.
- Repeat testing matters. Markers like TP53 can emerge or change over time, and treatment decisions must reflect your current biology.
- Request your genomic profile in writing. Always ask for a printed copy to review directly with your care team so nothing gets lost between appointments.
Disclaimer: The information provided in this article is for informational purposes only and is not intended to be a substitute for professional medical advice, diagnosis, or treatment. Outcomes4Me is not acting as your caregiver, and any suggestions or guidance offered should not replace the advice of your healthcare provider or qualified medical professional. Always seek the guidance of your physician or other qualified health provider with any questions you may have regarding a medical condition.
Personalized support for real care decisions
Understand your diagnosis, explore clinical trials, and track symptoms--all in one place.
Get started
Compare treatments, prepare for appointments, and track side effects—all in the app
Built for your diagnosis, Outcomes4Me gives you the tools to make confident, informed decisions—right when you need them.
Continue in app