

A muscle-invasive bladder cancer diagnosis lands differently than an early-stage one — and the decisions that follow carry real weight.
Muscle-invasive bladder cancer (MIBC) means the cancer has grown through the inner lining of the bladder and into the muscularis propria, the thick muscle wall. Because of this deeper invasion, muscle-invasive bladder cancer may require more aggressive surgical approaches, such as radical cystectomy, compared to non-muscle-invasive types, which is why muscle-invasive bladder cancer treatment demands a more aggressive and carefully considered response.
For decades, the standard answer was straightforward: remove the bladder. Radical cystectomy was considered the default for nearly every eligible patient, with little room for discussion. That’s changing. Advances in combined-modality therapy have put shared decision-making at the center of MIBC care. Rather than receiving a single recommendation, you’re now expected — and encouraged — to work alongside your oncology team to weigh options against your medical profile, priorities, and quality-of-life goals. Understanding what life looks like after different treatments is a meaningful part of that conversation.
The two primary paths — bladder removal and bladder preservation — each come with distinct trade-offs. Starting with the surgical option helps clarify exactly what you’d be choosing, or choosing away from.
Radical cystectomy: understanding the surgical gold standard
Radical cystectomy for bladder cancer has long been the benchmark treatment — a comprehensive surgery that removes the bladder entirely along with surrounding lymph nodes, and in many cases nearby reproductive organs. Before surgery, radical cystectomy is a surgical treatment option for muscle-invasive bladder cancer that has grown into the bladder wall or beyond. Your doctor may recommend additional treatments before or after surgery to reduce the risk of cancer returning. The appeal is straightforward: removing the primary tumor site eliminates the source of the disease, and for many patients and their providers, that offers a real sense of peace of mind that other approaches can’t fully replicate.
The surgery also requires a plan for how urine will leave the body. There are three main urinary diversion options:
- Ileal conduit — A short segment of intestine is used to route urine through a small opening in the abdomen into an external collection bag. It’s the most common diversion and generally requires less complex recovery.
- Neobladder — A new internal reservoir is constructed from intestinal tissue and connected to the urethra, allowing patients to urinate more naturally. It comes with a learning curve but preserves the closest thing to normal bladder function.
- Indiana pouch — An internal pouch that’s drained several times a day using a catheter through a small, discreet abdominal opening. No external bag is needed, but it requires consistent self-catheterization.
Each option carries its own tradeoffs, and the right choice depends on your anatomy, lifestyle, and overall health. Recovery, physically and emotionally, takes time. That context matters as you weigh this path against bladder-preserving approaches, which the next section explores in detail.
Evidence-based guidance powered by NCCN Guidelines®
Personalized treatment plans shaped by the latest oncology standards—tailored to your diagnosis.
Get started
View your personalized treatment plan in the Outcomes4Me app
Use your diagnosis to unlock personalized NCCN Guidelines®-aligned recommendations.
Continue in app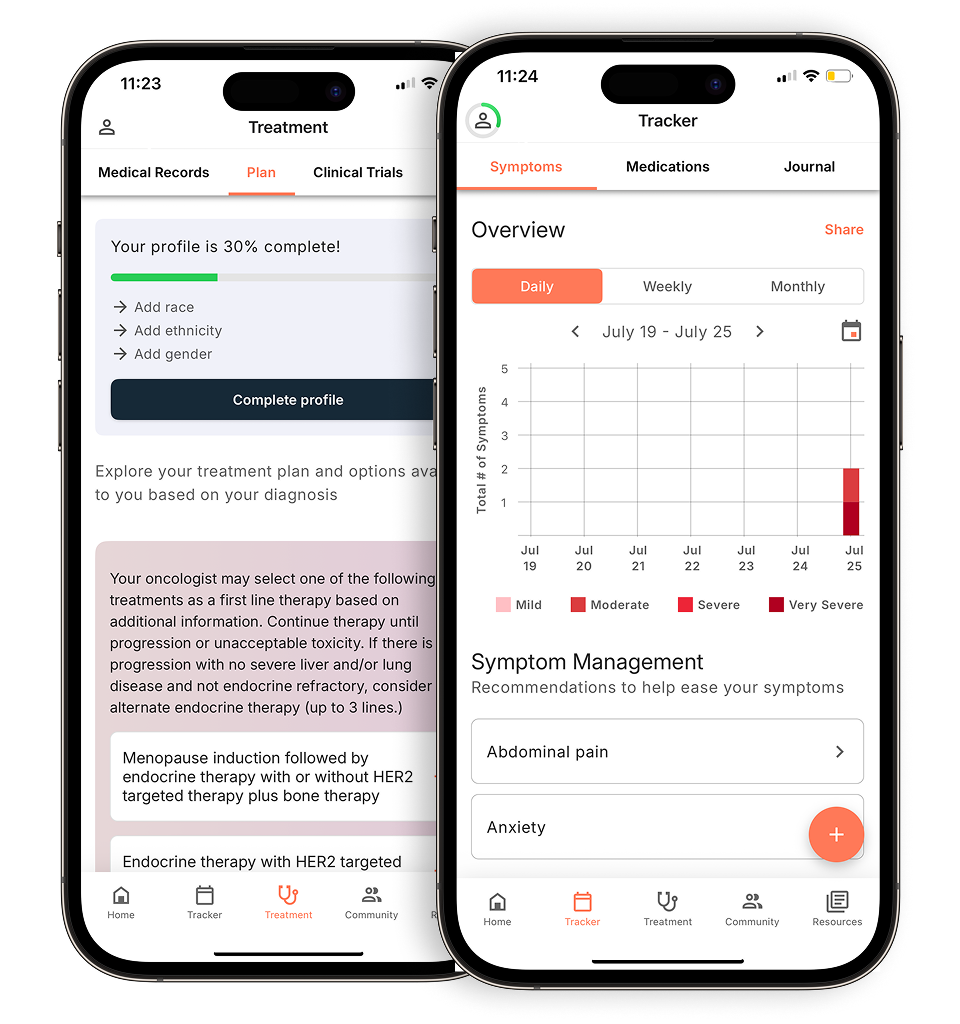
Bladder preservation: how trimodal therapy (TMT) works
Chemoradiation therapy combined with transurethral resection of bladder tumor has been used as a bladder-preserving approach for some patients with muscle-invasive bladder cancer, though long-term survival outcomes vary and additional research is needed to understand how well this approach works in routine clinical practice. For patients who qualify, this treatment path has become a credible alternative to surgery, with recent research showing comparable survival outcomes to radical cystectomy in selected patients.
Prong 1: maximal TURBT. The process begins with a transurethral resection of the bladder tumor (TURBT) — a procedure performed through the urethra that removes as much visible tumor tissue as possible. The goal isn’t just debulking; it’s creating the best possible conditions for what follows.
Prongs 2 and 3: concurrent radiation and chemotherapy. After TURBT, radiation targets the remaining tumor site while chemotherapy runs simultaneously. In trimodal therapy, certain drugs can enhance the effectiveness of radiation by increasing cancer cell sensitivity to treatment, potentially improving outcomes when combined with radiotherapy. Together, they work to eliminate residual disease and reduce the risk of recurrence.
The functional benefit is significant. Because the bladder stays intact, patients preserve natural urinary control and, in many cases, sexual function — outcomes that radical cystectomy can’t reliably offer. Keeping your own bladder means avoiding the lifelong adjustments that come with a urinary diversion.
Of course, not every patient is a strong candidate for this approach. The characteristics that make someone well-suited — or less suited — for TMT are worth understanding in detail.
Are you a candidate for preservation? The selection criteria
Not every patient with muscle-invasive bladder cancer is a strong candidate for trimodal therapy — and understanding who qualifies is just as important as understanding how it works. The best candidates share a specific clinical profile that makes bladder preservation both safe and effective.
According to BCAN, ideal candidates typically meet these criteria:
- Tumor size and number: A single, solitary tumor smaller than 5 cm responds better to chemoradiation than larger or multifocal disease
- No hydronephrosis: Blockage of the ureters — known as hydronephrosis — is often a contraindication for preservation therapy, as it signals more advanced local disease
- Complete TURBT: A visually complete transurethral resection before TMT begins improves response rates significantly
- Good baseline bladder function: Patients whose bladders function well before treatment tolerate radiation better and retain usable bladder capacity afterward
- No carcinoma in situ (CIS): Widespread CIS alongside the primary tumor can reduce the likelihood of a durable complete response
This profile also makes TMT a compelling option for older patients. Bladder preservation therapy with chemoradiation can be an option for elderly individuals with muscle-invasive bladder cancer, avoiding the need for major surgery, though outcomes may vary compared to other treatment approaches.
If TMT doesn’t achieve a complete response, salvage cystectomy remains an option — but it’s worth understanding what that means in practice. Salvage cystectomy performed after radiation is technically more complex than upfront surgery. Radiation changes the surrounding tissue, which can increase complication rates and make reconstruction more challenging. It’s a viable path, not a guaranteed one, and this possibility should factor into shared decision-making from the start.
Cancer care guidance for every step of your journey
Get treatment options, clinical trials, and support tailored to your diagnosis--all in one place.
Get started
See treatment options, manage symptoms, and stay informed—all in the app
View treatment options and trials personalized to your diagnosis—plus track progress in real time.
Continue in appPatients weighing these trade-offs can explore personalized treatment considerations to better understand how individual factors shape recommendations. As research continues to refine patient selection, emerging therapies — including immunotherapy — are beginning to change the calculus for those at high risk of recurrence, which we’ll explore next.
The role of immunotherapy and clinical trials in MIBC
Beyond the bladder preservation versus removal decision, a new layer of treatment is reshaping what’s possible for patients with muscle-invasive bladder cancer — one driven by immunotherapy and clinical research.
For patients who complete definitive treatment but remain at high risk of recurrence, adjuvant immunotherapy has become an increasingly important option. Nivolumab, a checkpoint inhibitor, is now approved for high-risk MIBC patients following radical cystectomy. It works by helping your immune system recognize and attack any remaining cancer cells — extending the window before recurrence in a meaningful way.
Clinical trials are pushing the boundaries even further. Researchers are actively testing combinations of trimodal therapy with immunotherapy agents, exploring whether adding checkpoint inhibitors to the standard chemotherapy-radiation protocol can drive even deeper responses. Early results are encouraging, one treatment approach using slow-release gemcitabine showed that cancer disappeared in approximately 82% of patients with high-risk, treatment-resistant bladder cancer, though the cancer remained absent in about half of these patients one year later.
Finding the right trial, however, isn’t straightforward. Eligibility often depends on specific genetic markers and tumor characteristics — factors that vary significantly between patients. That’s where tools like Outcomes4Me can make a real difference. The platform helps patients identify clinical trials matched to their specific diagnosis, biomarkers, and treatment history, cutting through the complexity of trial databases to surface relevant options quickly.
Understanding these emerging possibilities is important — but so is knowing how to act on them. The next section brings together everything covered so far into a clear, practical summary.
The bottom line: what you need to know
Choosing between bladder removal and preservation is one of the most consequential decisions in muscle-invasive bladder cancer care — and there’s no single right answer for every patient.
Radical cystectomy remains the most established treatment for MIBC, with decades of outcomes data behind it. It’s a curative-intent surgery that eliminates the bladder but requires permanent urinary diversion — a reality that shapes daily life in meaningful ways. If you’re weighing what recovery actually looks like, real accounts from others who’ve been through it can offer perspective no clinical summary fully captures.
Trimodal therapy offers a clinically validated alternative for patients who meet the right criteria. For muscle-invasive bladder cancer with certain variant histologies, bladder-preserving chemoradiotherapy can achieve comparable overall survival outcomes to radical cystectomy, though it requires rigorous follow-up and carries its own recurrence risks, as covered in earlier sections.
Genomic testing and clinical trials aren’t optional extras — they’re increasingly central to personalized MIBC care. Understanding your tumor’s molecular profile can open doors to targeted therapies and emerging immunotherapy combinations that standard protocols may not include. As the Outcomes4Me Editorial Board notes, “The best treatment is the one that aligns with both the clinical stage of the cancer and the patient’s long-term quality of life goals.”
A second opinion from a multidisciplinary team — ideally including a urologist, radiation oncologist, and medical oncologist — isn’t a sign of doubt. It’s standard practice at major cancer centers and often the step that reveals options a patient didn’t know they had. The complexity of this decision is exactly why the next section focuses on the questions worth bringing to that conversation.
Taking control: questions for your oncology team
Navigating a muscle-invasive bladder cancer diagnosis means asking the right questions — and going into appointments prepared can make all the difference in the care you receive.
Before your next visit, consider raising these questions directly with your oncology team:
- “Am I a candidate for bladder preservation based on my tumor size and location?” Not every patient is eligible for trimodality therapy. Understanding whether your tumor characteristics meet the criteria for bladder-sparing treatment is the starting point for any informed decision.
- “What is the risk of recurrence if we choose TMT over surgery?” Recurrence remains a real possibility after radical cystectomy, even when no cancer is visible at the time of surgery, which is why follow-up care is an important part of treatment.
- “Are there clinical trials available that combine immunotherapy with my treatment?” Immunotherapy research for bladder cancer is advancing rapidly, with investigational approaches showing potential to improve outcomes for patients with this disease.
- “What does recovery look like either way — and how will each path affect my day-to-day life?” Quality of life is a clinically relevant factor, not just a personal preference.
Your care team has the expertise — but you have the right to ask questions, seek clarity, and be part of every decision.
Evidence-based treatment options for muscle-invasive bladder cancer include surgery, chemotherapy, radiation therapy, immunotherapy, and targeted therapy, which you and your cancer care team will consider together based on your cancer stage, grade, overall health, and preferences. Use the Outcomes4Me app to track your records, organize your questions, and get a personalized treatment roadmap — so you walk into every appointment informed, prepared, and in control.
Disclaimer: The information provided in this article is for informational purposes only and is not intended to be a substitute for professional medical advice, diagnosis, or treatment. Outcomes4Me is not acting as your caregiver, and any suggestions or guidance offered should not replace the advice of your healthcare provider or qualified medical professional. Always seek the guidance of your physician or other qualified health provider with any questions you may have regarding a medical condition.
Personalized support for real care decisions
Understand your diagnosis, explore clinical trials, and track symptoms--all in one place.
Get started
Compare treatments, prepare for appointments, and track side effects—all in the app
Built for your diagnosis, Outcomes4Me gives you the tools to make confident, informed decisions—right when you need them.
Continue in app




