

When evaluating biochemical recurrence in prostate cancer, it’s important to understand the key differences. A rising PSA after prostatectomy is one of the most disorienting moments in prostate cancer care, but biochemical recurrence in prostate cancer is a clinically defined, manageable event.
After radical prostatectomy, the prostate gland is removed entirely. Without prostate tissue present, PSA levels should fall to undetectable levels, typically below 0.1 ng/mL. Your care team will monitor this number closely through regular blood tests in the months following surgery. An undetectable PSA is the goal.
What changes the picture is a rising number. Biochemical recurrence (BCR) is defined as a PSA level of 0.2 ng/mL or higher confirmed on two consecutive tests. That threshold matters: a single elevated reading can reflect lab variability, so the two-test confirmation standard exists to reduce unnecessary alarm.
For many patients, that number triggers an anxiety gap: the fear that surgery didn’t work, that cancer is spreading unchecked. That fear is completely understandable. However, a BCR diagnosis is not the same as a clinical recurrence, and it doesn’t mean the situation is out of control. What a rising PSA actually signals depends on several factors, and understanding those factors is where informed decision-making begins.
The critical distinction is where that PSA signal is coming from: and that question shapes everything about what happens next.
Deciphering the rise: local recurrence vs. distant spread
A rising PSA after prostate cancer surgery doesn’t tell you where the cancer is: and that distinction changes everything about what comes next. When PSA climbs after a prostatectomy, the cause typically falls into one of three clinical scenarios, each carrying very different implications for treatment and prognosis.
Scenario 1, local recurrence is the most treatable outcome. Here, cancer cells remain in the prostate bed, the tissue area where the prostate once sat. Salvage radiation therapy targets the prostate bed directly for local recurrence, and for many patients with local recurrence, salvage radiation therapy can achieve an undetectable PSA. This is the scenario most providers hope for.
Scenario 2, distant metastasis means microscopic disease has spread beyond the pelvis, most often to lymph nodes or bone. This doesn’t mean the cancer is immediately life-threatening, but it does require a more systemic treatment strategy. Providers increasingly use PSMA-PET scans to detect spread in prostate cancer recurrence.
Scenario 3, benign remnant tissue is rare but worth knowing. Occasionally, a small amount of non-cancerous prostate tissue is left behind during surgery and continues producing PSA at low, stable levels.
Timing offers a meaningful clue about which scenario you’re facing. A rapidly rising PSA (doubling time of approximately 9 months or less) suggests more aggressive disease and carries greater risk for developing metastases, which is why your doctor may recommend prompt evaluation and treatment discussion. When a PSA rise occurs after prostatectomy and cancer is thought to still be localized to the prostate area, radiation therapy to where the prostate was may be an option.
Evidence-based guidance powered by NCCN Guidelines®
Personalized treatment plans shaped by the latest oncology standards—tailored to your diagnosis.
Get started
View your personalized treatment plan in the Outcomes4Me app
Use your diagnosis to unlock personalized NCCN Guidelines®-aligned recommendations.
Continue in app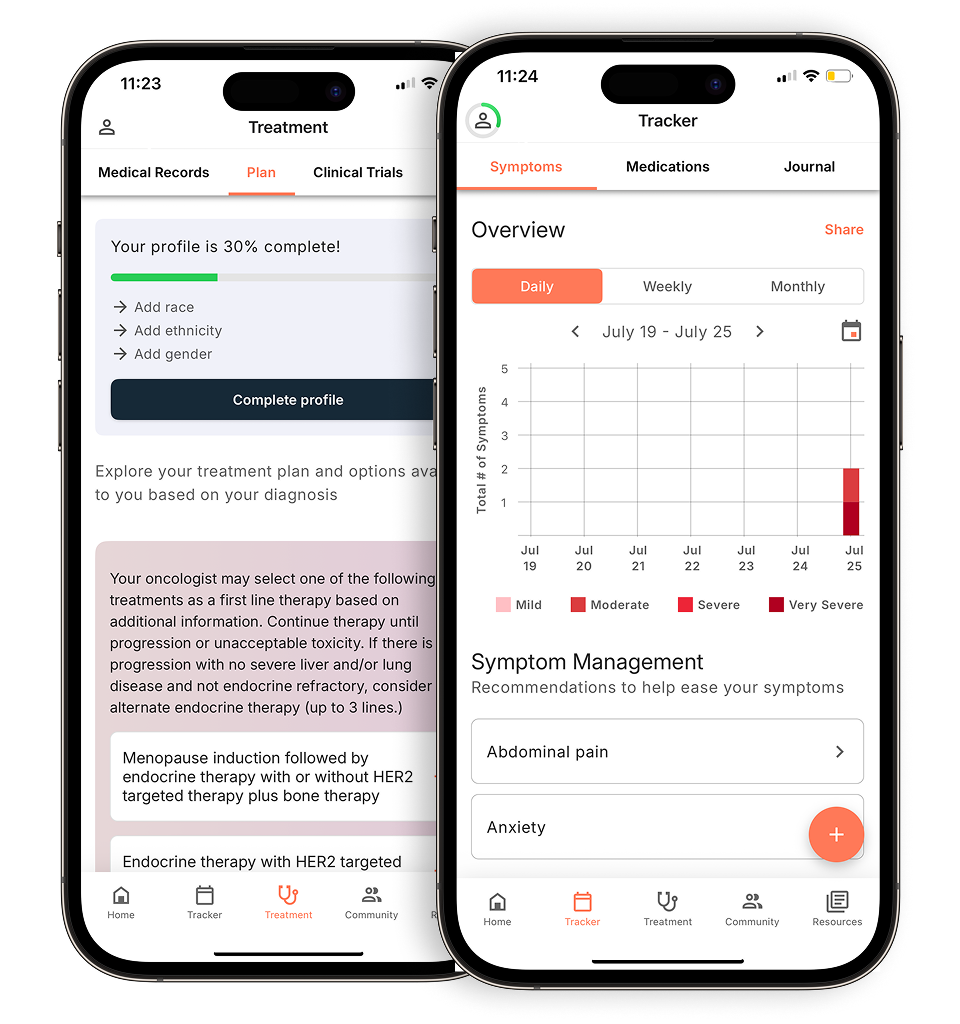
Understanding which scenario applies is the foundation of personalized care, but timing alone isn’t the whole picture. How fast PSA is rising matters just as much as when it started.
The power of velocity: why PSA doubling time matters
The absolute PSA number tells only part of the story: how fast it’s rising tells you far more about what’s actually happening.
PSA doubling time (PSADT) measures how quickly your PSA level doubles in months. For patients tracking PSA doubling time after prostatectomy, this metric is often more meaningful than any single reading. It shifts the conversation from a snapshot to a trend, and that trend carries real clinical weight.
A PSADT of less than six to ten months is associated with a significantly higher risk of metastasis and a more aggressive disease course. Research published in JAMA found that men with a PSADT under three months face a substantially elevated risk of prostate cancer-specific mortality, a finding that underscores why oncologists treat velocity as a key decision-making variable. On the other end of the spectrum, a slow rise, a PSADT measured in years, may never cause symptoms within a patient’s lifetime, which is why active monitoring, rather than immediate intervention, is sometimes the right call.
Calculating PSADT requires at least two PSA readings taken weeks apart, then applying a standard formula your care team can run. What matters most is consistency, tracking values at regular intervals so the trend becomes visible. Regular PSA monitoring after prostatectomy allows you and your care team to track trends over time and discuss what rising PSA levels mean for your individual situation.
Once PSADT points toward the need for further evaluation, the next critical question is where the recurrence is, which is exactly where modern imaging has transformed what’s possible.
New standards in imaging: the PSMA PET revolution
Modern imaging has fundamentally changed what’s possible when PSA begins to rise, and that shift matters enormously for deciding between targeted treatment and a blind approach.
Conventional imaging modalities such as CT scans and bone scans are often insufficient for detecting recurrent prostate cancer, particularly when PSA levels are below 5 ng/mL. At PSA levels below 1.0 ng/mL, conventional scans frequently miss the recurrence entirely. For patients and providers trying to choose between adjuvant vs. salvage radiotherapy, that missing information can lead to decisions made in the dark.
PSMA PET scan (prostate-specific membrane antigen positron emission tomography) changes that equation. This next-generation scan uses a radioactive tracer that binds to a protein found on the surface of prostate cancer cells, making even tiny clusters of disease visible. PSMA PET can identify the location of recurrence in up to 75% of patients with a PSA between 0.5 and 1.0 ng/mL.
Cancer care guidance for every step of your journey
Get treatment options, clinical trials, and support tailored to your diagnosis--all in one place.
Get started
See treatment options, manage symptoms, and stay informed—all in the app
View treatment options and trials personalized to your diagnosis—plus track progress in real time.
Continue in appWhy location changes everything. Knowing where the cancer is, confined to the prostate bed, in a nearby lymph node, or at a distant site, transforms a generalized treatment plan into a precise one. A patient with disease limited to the prostate bed becomes a strong candidate for targeted salvage radiation. Men with lymph node metastases after prostatectomy who lack high-risk features such as seminal vesicle invasion, Gleason score of 9 or greater, three or more positive lymph nodes, or positive surgical margins may be managed with observation rather than receiving intensive adjuvant therapy. That precision also opens the door to clinical trials testing newer, highly targeted therapies.
If your PSA is rising after prostatectomy, it’s worth asking your provider directly whether you’re a candidate for a PSMA PET scan.
Choosing your path: salvage radiation vs. hormone therapy
When PSA begins to rise after surgery, two core treatment strategies come into focus: and understanding the trade-offs between them is essential for making an informed decision with your care team.
Salvage radiotherapy (SRT) targets the prostate bed directly, with the goal of permanently eliminating residual cancer cells before they spread further. It’s widely considered the best chance at a durable cure for localized recurrence. The key insight from recent research is when to use it: research comparing adjuvant radiation (given immediately after surgery) with early salvage radiation (given when PSA rises) suggests that adjuvant radiation may offer superior outcomes in preventing biochemical recurrence and distant metastases, though both approaches carry potential side effects that warrant individual patient discussion.
Androgen deprivation therapy (ADT) is designed to lower testosterone levels, based on the idea that prostate cancer cells may depend on this hormone to grow. Your care team can discuss whether this approach might be appropriate for your situation. Hormone therapy combined with radiation may delay the development of metastasis, offering a window of time to pursue additional treatment options tailored to your specific risk factors.
Knowing whether cancer is confined to the prostate bed or has spread elsewhere is where PSMA PET scanning becomes valuable. It helps determine whether cancer is confined to the prostate bed (favoring SRT) or has spread elsewhere (shifting the strategy toward systemic therapy).
Clinical trials are also worth exploring at this stage. Next-generation therapies including PARP inhibitors, novel hormonal agents, and PSMA-targeted treatments are actively being studied in men with biochemical recurrence. Some patients and care teams discuss clinical trials as a potential option when managing a rising PSA after prostatectomy. Ask your oncologist whether a trial might be appropriate to explore as part of your individual treatment plan.
The right path forward depends on your PSA doubling time, imaging findings, and individual risk profile, all the threads we’ve been following throughout this article. Pulling them together into a clear, personalized picture is exactly what the next section addresses.
The bottom line: what you need to know now
A rising PSA after prostatectomy calls for informed action, and understanding a few core principles makes all the difference in how you respond.
The definition of PSA failure most widely used today places the threshold at 0.2 ng/mL, confirmed on two separate measurements. That number matters, but it’s only the starting point. What your care team will watch just as closely is how fast that number climbs. A slow PSA doubling time generally signals lower-grade disease and broader treatment options. A rapid doubling time may indicate more aggressive disease that warrants faster intervention.
Knowing where the recurrence is located is equally critical. PSMA PET scans have transformed early detection by identifying lesions that older imaging simply missed, allowing your team to distinguish local recurrence from distant spread before choosing a treatment path.
For many men, salvage radiation therapy remains a genuinely curative option particularly when started early, while PSA levels are still low. Hormone therapy may be added depending on risk factors, but the decision isn’t one-size-fits-all. PSA monitoring every 3–6 months for the first several years after prostatectomy, combined with discussions with your doctor about what rising PSA means and what treatment options may be appropriate, helps guide personalized next steps.
Personalized data tracking ties everything together. Tools that align your results with treatment guidelines help ensure no meaningful trend goes unnoticed between appointments. As you gather your lab history and prepare your next questions, the right resources can turn data into clarity.
Empowering your next consultation
A rising PSA doesn’t have to feel disorienting. It becomes manageable the moment you walk into your next appointment prepared. Start by gathering your full lab history, including all post-surgical PSA values with their dates, along with your original pathology report. These documents give your care team the raw material they need to calculate how quickly your PSA is doubling, one of the most important factors in deciding when and how to act.
Walking in with the right questions transforms a follow-up visit into a strategy session. Consider asking your provider directly:
- “What is my PSA doubling time, and what does it tell us about my risk?”
- “Am I a candidate for a PSMA PET scan to identify where the recurrence is located?”
- “Based on my pathology and PSADT, should I consider salvage radiation now or monitor further?”
Disclaimer: The information provided in this article is for informational purposes only and is not intended to be a substitute for professional medical advice, diagnosis, or treatment. Outcomes4Me is not acting as your caregiver, and any suggestions or guidance offered should not replace the advice of your healthcare provider or qualified medical professional. Always seek the guidance of your physician or other qualified health provider with any questions you may have regarding a medical condition.
Personalized support for real care decisions
Understand your diagnosis, explore clinical trials, and track symptoms--all in one place.
Get started
Compare treatments, prepare for appointments, and track side effects—all in the app
Built for your diagnosis, Outcomes4Me gives you the tools to make confident, informed decisions—right when you need them.
Continue in app



