When SCLC returns: navigating the emotional and clinical shift
A small cell lung cancer diagnosis is hard enough, but hearing that it has come back can feel like the ground shifting beneath you. What’s important to hold onto, however, is that recurrence doesn’t mean the end of options.
SCLC often responds well to first-line treatment, but recurrence is common. How your care team responds depends critically on the specific nature of that recurrence.
As recent research confirms, SCLC carries both a high initial response rate and a high frequency of recurrence. That clinical reality shifts the goal of treatment. Where first-line therapy is often approached with curative intent, aiming to eliminate disease, recurrence typically focuses on disease control, preserving quality of life, and extending the time you feel well.
This shift prioritizes what matters most at this stage: keeping you functional, managing symptoms, and keeping meaningful options on the table.
One of the most consequential factors in that recalibration is understanding what kind of recurrence you’re dealing with. Not all relapses are clinically equivalent, and your treatment strategy will differ significantly depending on timing and biology. Before your care team can build that strategy, you need to recognize the early signals, which means knowing the signs of small cell lung cancer recurrence and understanding why catching them promptly makes a real difference in what comes next.
Signs of small cell lung cancer recurrence: what to watch for
Recognizing small cell lung cancer recurrence early can make a meaningful difference in how quickly you and your care team respond. Because SCLC tends to spread rapidly, knowing which symptoms to take seriously and when to call your provider matters.
Some patients with small cell lung cancer recurrence experience respiratory or chest symptoms, which may prompt a conversation with your care team about whether imaging or other follow-up tests are needed. A new or worsening cough, increased chest pain, or shortness of breath can be easy to dismiss as lingering effects of treatment, but they deserve attention.
Beyond respiratory signs, watch for the following:
- Unexplained weight loss, losing pounds without a change in diet or activity level
- Profound fatigue, exhaustion that rest doesn’t relieve
- Headaches, vision changes, or confusion, neurological symptoms that may point to brain metastases, a particularly common concern with SCLC
Neurological symptoms should never be ignored. SCLC has a high likelihood of spreading to the central nervous system, so any new cognitive or sensory changes warrant prompt evaluation.
Many cases are caught through routine surveillance imaging before patients notice anything at all. These scheduled scans are your safety net for recurrence that is actively progressing without clear physical warning signs.
Understanding what signs to watch for is the first step. The next equally important question is when the cancer comes back, and that timing shapes everything about your treatment options.
Evidence-based guidance powered by NCCN Guidelines®
Personalized treatment plans shaped by the latest oncology standards—tailored to your diagnosis.
Get started
View your personalized treatment plan in the Outcomes4Me app
Use your diagnosis to unlock personalized NCCN Guidelines®-aligned recommendations.
Continue in app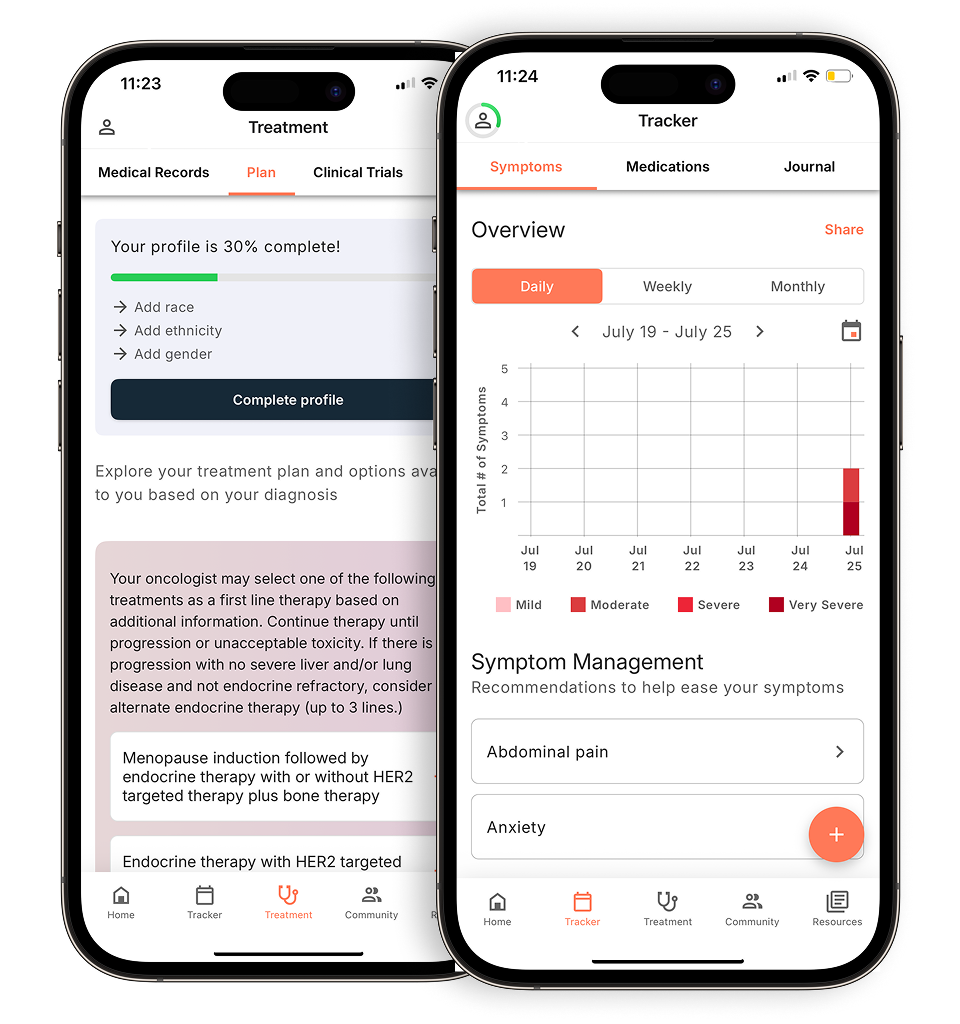
The 6-month rule: sensitive vs. resistant relapse
How quickly SCLC returns after initial treatment is one of the most important factors shaping what comes next.
Oncologists use a well-established framework to classify relapse based on timing, and understanding it helps you make sense of why your care team may be recommending one treatment path over another.
Key distinction: If cancer returns more than six months after completing first-line platinum-based chemotherapy, it is classified as a sensitive relapse. If cancer continues to grow during initial chemotherapy treatment or returns within less than six months after chemotherapy has stopped, it may be less likely to respond to additional chemotherapy, and your doctor may recommend clinical trials or alternative treatment options.
Platinum-sensitive SCLC carries a meaningfully better prognosis. Clinical trials in relapsed small cell lung cancer show that treatment outcomes can differ based on whether tumors are platinum-sensitive or platinum-resistant, highlighting the importance of understanding your cancer’s treatment history when planning next steps. Patients with a longer treatment-free interval after initial platinum chemotherapy may be candidates for re-treatment with platinum agents, as timing of recurrence is an important factor in determining subsequent treatment options.
Refractory relapse signals that the tumor has already found ways to survive platinum exposure. Re-using those same drugs is unlikely to work and could waste critical treatment time. In these cases, your care team will move directly to alternative agents rather than revisiting what’s already been tried.
This timing-based classification functions as a clinical decision tool, directly influencing which therapies are on the table. Understanding where your relapse falls on this spectrum sets the foundation for the conversation about second-line treatment options, which we’ll explore in the next section.
Second-line treatment options: beyond the first round
Choosing the right second-line treatment for SCLC depends heavily on the sensitive vs. resistant distinction covered earlier, but knowing which drugs are actually on the table helps you ask sharper questions at your next appointment.
Lurbinectedin (Zepzelca) is a common second-line option for many patients with relapsed SCLC. Granted accelerated FDA approval in 2020 for metastatic SCLC following progression on platinum-based chemotherapy, lurbinectedin (Zepzelca) is a chemotherapy drug that may be used to treat small cell lung cancer when the cancer worsens or comes back after initial treatment. Lurbinectedin is given as an intravenous infusion for recurrent small cell lung cancer and has a more manageable side effect profile than older chemotherapy regimens, an important consideration when patients are already managing the cumulative toll of first-line treatment.
Cancer care guidance for every step of your journey
Get treatment options, clinical trials, and support tailored to your diagnosis--all in one place.
Get started
See treatment options, manage symptoms, and stay informed—all in the app
View treatment options and trials personalized to your diagnosis—plus track progress in real time.
Continue in appTopotecan remains the longer-standing option and is available in both oral and IV forms. While it’s been used for decades in relapsed SCLC, its side effect profile, particularly hematologic toxicities like anemia, neutropenia, and thrombocytopenia, can be challenging to manage. The oral formulation offers convenience, but clinical benefit is comparable to IV delivery. For patients with recurrent small cell lung cancer, topotecan is one of several chemotherapy options that may be used after initial treatment, particularly when other drugs are not available or suitable.
Immunotherapy also enters the picture here. Atezolizumab is a PD-L1 inhibitor that can be used as part of first-line treatment for advanced SCLC, either in combination with chemotherapy or continued alone as maintenance therapy. As treatment science continues to advance rapidly, emerging targeted approaches, including novel agents matched to specific tumor biology, are increasingly worth exploring through clinical trials, which we’ll look at next.
Why clinical trials are a proactive choice for SCLC
Clinical trials are one of the most direct paths to therapies that aren’t yet available through standard care. For patients with recurrent SCLC, where the debate between lurbinectedin vs. topotecan often defines second-line treatment, trials open a third lane entirely.
Emerging research highlights two particularly promising directions:
- DLL3-targeted agents, DLL3 is overexpressed in most SCLC tumors, making it an attractive target. Antibody-drug conjugates designed to target tumor antigens are now in active trials, with early results showing meaningful tumor responses in heavily pretreated patients with recurrent small cell lung cancer.
- SCLC molecular subtypes, Researchers have identified four SCLC subtypes: SCLC-A, SCLC-N, SCLC-P, and SCLC-Y, each driven by distinct transcription factors. Trial eligibility is increasingly being structured around SCLC subtypes, which means your tumor’s biology may now determine which experimental therapy fits best.
- PARP inhibitors in select subsets, In tumors with specific DNA-repair deficiencies, PARP inhibition is showing early promise as a combination strategy.
Matching your genetic markers to an open trial used to require hours of manual searching, but digital platforms now make that process far more manageable. Tools like trial databases let you filter trials by tumor markers, prior treatment history, and location, giving you a clearer picture of what’s actually available to you right now.
The right trial, at the right time, can be genuinely treatment-altering. The next section pulls the key takeaways together to help you and your care team approach recurrence with a clear strategy.
The bottom line: key takeaways for navigating recurrence
Navigating SCLC recurrence is complex, but a few core principles can help you and your care team make faster, more confident decisions. The single most important factor shaping your next treatment is how much time has passed since your last platinum-based chemotherapy ended. That interval, sensitive vs. resistant, determines which drugs are likely to work and how aggressively your team will approach second-line therapy.
Lurbinectedin and topotecan remain the two primary FDA-approved second-line options, each with a different profile of efficacy and tolerability. As covered earlier, your oncologist will weigh your platinum sensitivity, performance status, and prior side effects before recommending one over the other. Neither is a universal answer, which is exactly why SCLC clinical trials have become such a meaningful part of the treatment landscape. Emerging therapies, including bispecific T-cell engagers and DLL3-targeting agents, are actively being studied and are accessible through enrollment in a clinical trial before they reach standard care.
One area that’s sometimes deprioritized in conversations about second-line treatment is palliative care. Early integration of palliative care alongside active treatment improves quality of life by managing symptoms like breathlessness, fatigue, and pain rather than waiting until treatment options are exhausted. Palliative care focuses on staying functional enough to keep fighting.
Knowing these pillars, timing, drug options, trials, and symptom management, puts you in a much stronger position to have productive conversations with your oncology team. The next section offers specific questions to bring to your next appointment.
Taking control: questions to ask your oncology team
Your next appointment is one of the most powerful tools you have, and arriving with the right questions can meaningfully shape the decisions that follow. As previous sections have outlined, the time to relapse after first-line therapy defines which treatment paths are open to you. Translating that clinical reality into a focused conversation with your care team is where informed decision-making begins.
Start with the foundational question: “Is my recurrence considered platinum-sensitive?” The answer to this single question determines whether re-treatment with platinum-based chemotherapy is viable or whether your care team needs to pivot to second-line options like topotecan or lurbinectedin. Don’t assume this classification has been communicated, ask directly and confirm the timing that informed that determination.
From there, ask: “What are the specific goals of this second-line treatment?” Is the aim to reduce tumor burden, manage symptoms, or extend progression-free survival? Understanding the intent behind a regimen helps you weigh its side-effect profile against realistic outcomes and gives you a clearer basis for comparing options.
Finally, ask: “Are there clinical trials available for my specific SCLC subtype?” Recent research continues to identify distinct SCLC molecular subtypes, and trial eligibility is increasingly subtype-specific. Your oncologist may not raise this proactively, which makes it essential that you do.
Disclaimer: The information provided in this article is for informational purposes only and is not intended to be a substitute for professional medical advice, diagnosis, or treatment. Outcomes4Me is not acting as your caregiver, and any suggestions or guidance offered should not replace the advice of your healthcare provider or qualified medical professional. Always seek the guidance of your physician or other qualified health provider with any questions you may have regarding a medical condition.
Personalized support for real care decisions
Understand your diagnosis, explore clinical trials, and track symptoms--all in one place.
Get started
Compare treatments, prepare for appointments, and track side effects—all in the app
Built for your diagnosis, Outcomes4Me gives you the tools to make confident, informed decisions—right when you need them.
Continue in app