A colorectal cancer diagnosis requires you to ask the right questions. The “fog of diagnosis” is real: shock, grief, and information overload can make every decision feel urgent and impossible at the same time. But in practice, the most effective step you can take is to slow down deliberately, organize your thinking, and treat this period as a logistics challenge rather than a race to absorb every medical detail about your condition.
That means focusing on the medical decisions that actually move you forward rather than getting overwhelmed by general disease education. Knowing which questions to ask your oncologist about colorectal cancer staging, treatment sequencing, and specialist referrals will reduce mental fatigue far more than reading every available article. Your energy is finite; protect it.
The goal of everything that follows is to help you move from a passive recipient of information to an active participant in your personalized care plan.
Decision 1: Selecting your multidisciplinary care team
The single most important step after a colorectal cancer diagnosis is assembling the right group of specialists around you, rather than scheduling treatment.
A single physician can be exceptional and still lack the breadth of perspective your case demands. A multidisciplinary team brings together a medical oncologist, who manages systemic therapy like chemotherapy or immunotherapy, a colorectal surgeon, who handles localized tumor removal, and a radiologist, who interprets imaging to guide every decision.
Requesting a second opinion is a standard safety check. Before any second-opinion consultation, get copies of your medical records, imaging, and pathology reports. This is your right as a patient, and most institutions can fulfill the request quickly.
Evaluating facility expertise and support staff
Where you receive care shapes your colorectal cancer outcomes. Facilities differ in their level of expertise.
Before your colorectal cancer surgeon consultation, ask about the surgeon’s experience performing colorectal cancer operations and whether the treatment facility performs a high volume of these procedures. Once you know where your care will happen, the next step is knowing exactly what to ask the specialists in that room.
Questions to ask your potential oncologist
The right medical oncologist for colorectal cancer treatments is credentialed, communicative, experienced with your specific case type, and backed by a support system that extends beyond the exam room.
When you meet a potential oncologist, bring three direct questions. How many cases like mine do you treat annually? What’s the after-hours protocol if I experience side effects? And does your practice have a dedicated social worker or financial counselor on site? Review what specialists typically recommend before your first consultation, so you walk in prepared. Once you’ve vetted your care team and facility, the next critical step is understanding the staging results that will define your entire treatment roadmap.
Decision 2: Decoding your pathology and staging results
Colorectal cancer staging shapes every subsequent choice in your colorectal cancer treatment plan, from surgical scope to whether systemic therapy enters the picture at all.
Doctors use staging to determine how far your cancer has spread, which helps guide your treatment plan. The stage is based on the size of the tumor, whether it has spread to lymph nodes, and whether it has spread to distant organs. Stage 1 disease, where cancer is confined to the inner layers of the colon or rectum, typically points toward localized removal with close monitoring to follow. Stage 4, where cancer has spread to distant organs, requires systemic management to control disease across the body rather than excising a single site. For Stage 3 colon cancer, lymph node involvement is a key factor, and adjuvant chemotherapy following surgery is a standard part of treatment.
Evidence-based guidance powered by NCCN Guidelines®
Personalized treatment plans shaped by the latest oncology standards—tailored to your diagnosis.
Get started
View your personalized treatment plan in the Outcomes4Me app
Use your diagnosis to unlock personalized NCCN Guidelines®-aligned recommendations.
Continue in app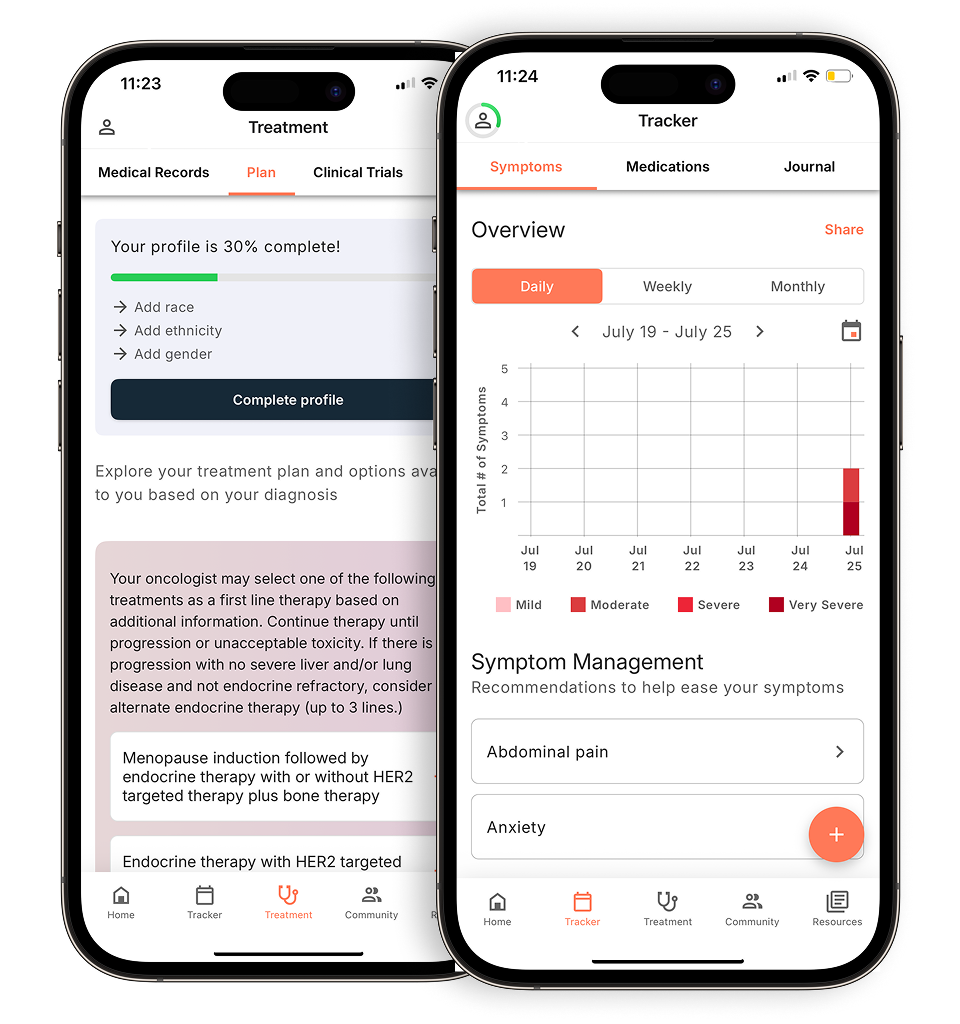
Biomarkers and genetic testing add another layer of precision your care team will review alongside stage. MSI (microsatellite instability) and dMMR (mismatch repair deficiency) status can determine whether immunotherapy is appropriate, a distinction that changes the entire treatment trajectory. These are foundational to building a genuinely personalized care plan.
For early-stage patients, your care team may work toward a goal sometimes called NED, or No Evidence of Disease. Ask your doctors what specific goals they are setting for your treatment. Understanding that target before treatment begins gives you a concrete benchmark to ask about at every follow-up. As you absorb these results, knowing what not to read into them is just as important, and that’s exactly where many patients stumble first.
Common mistakes in understanding lab reports
Confusing “grade” with “stage” is one of the most common mistakes patients make when figuring out what to do after a colorectal cancer diagnosis.
Grade describes how abnormal cancer cells look under a microscope; stage describes how far the disease has traveled. They’re related but distinct, and your treatment options depend on both. A second frequent trap is over-relying on general internet survival statistics that predate current targeted therapies. Those figures often don’t reflect what’s possible with a truly personalized care plan today. Another common mistake is treating a single scan result as a definitive verdict. After your colorectal cancer diagnosis, your care team will order multiple tests to determine the size and extent of your cancer. These tests work together to give your doctors a complete picture of your cancer and help guide your treatment plan.
Finding support after cancer diagnosis can help you manage the emotional challenges that arise when results feel uncertain. The clearer picture, the one that actually drives treatment, lives in your molecular data, which is exactly what the next layer of your report addresses.
Biomarkers: the blueprint for modern treatment
Your molecular data becomes the most actionable layer of your entire report as your care team builds your personalized treatment plan.
CEA (Carcinoembryonic Antigen) levels give your care team a baseline measurement to track over time, but a single elevated number isn’t a verdict. Where molecular testing becomes decisive is with mutations like KRAS and BRAF: if either is present, certain targeted therapies won’t work, and your personalized care plan routes around them entirely. Requesting a full molecular profile early, before treatment begins, ensures no option is ruled in or out by assumption rather than evidence.
Decision 3: Weighing immediate treatment vs. clinical trials
Your care team should discuss clinical trials as an option. Asking about them directly is one of the smartest moves you can make before treatment begins.
Standard of care (SOC) protocols represent the best-validated treatments available, and for many patients, they’re the right starting point. But clinical trials often provide access to more precisely targeted therapy before it reaches routine practice. Asking your care team whether a trial fits your molecular profile costs nothing and could meaningfully expand your options.
Adjuvant chemotherapy is where this trade-off gets most personal. At stage 2B, the benefit-to-risk calculation for adjuvant chemotherapy isn’t straightforward. Some patients gain measurable protection against recurrence, while others face side effects with limited added benefit. Your personalized care plan should factor in your MSI status and overall health, not just the stage number alone.
Cancer care guidance for every step of your journey
Get treatment options, clinical trials, and support tailored to your diagnosis--all in one place.
Get started
See treatment options, manage symptoms, and stay informed—all in the app
View treatment options and trials personalized to your diagnosis—plus track progress in real time.
Continue in appWhen learning how to prepare for colon cancer treatment, bring a specific question to your oncologist. Is there a trial that matches my biomarker profile, and what does the SOC comparison look like? On immunotherapy specifically, it’s worth understanding whether your tumor’s MMR (mismatch repair) status makes you a stronger candidate than traditional chemotherapy alone would suggest. Your care team can help you explore clinical trials that may be available for your colorectal cancer and discuss which trials might be appropriate for your specific situation. With your treatment options mapped, the next decision, whether surgery comes first, follows directly from this framework.
When is surgery the first step?
Understanding when surgery leads versus follows other treatments is a decision that shapes your entire personalized care plan, rather than assuming every colorectal cancer diagnosis moves straight to the operating room.
For early-stage disease, surgery is often the primary intervention. Laparoscopic-assisted colectomy involves smaller incisions than open surgery, which may allow you to recover faster and leave the hospital sooner. Laparoscopic approaches generally mean less post-operative pain and a faster return to daily activity, though your care team will determine which technique fits your tumor’s location and complexity.
For locally advanced tumors, particularly rectal cancers, neoadjuvant therapy (chemotherapy, radiation, or both administered before surgery) may shrink the tumor first, improving the likelihood of a clean surgical margin. Understanding that “treatment before surgery” is a deliberate, evidence-based strategy helps you stay oriented when the timeline feels longer than expected. The good news is that clinical trials are increasingly relevant to this phase too.
Clinical trial myths and realities
Clinical trials test new treatments to see if they work better than current standard approaches, and many trials compare new therapies directly against the treatments doctors use today.
This distinction matters enormously for any new colon cancer patient guide worth following. The “guinea pig” fear is understandable, but it reflects a common misread of how trials are structured. Your personalized care plan doesn’t get replaced; it gets built upon. And because trial sponsors typically cover the cost of investigational drugs and protocol-required procedures, your financial exposure is often narrower than you’d expect. Confirming that split with your care team before enrollment is essential.
Some of the treatments now used in colorectal cancer care were first studied in clinical trials, which may have contributed to improvements in outcomes over recent years. With your treatment framework in place, the next layer of preparation, one that most patients underestimate, involves the financial and logistical infrastructure that keeps you in treatment over the long term.
Decision 4: Building your personal support and financial infrastructure
Many patients find that having structured support, whether from family, friends, or community resources, helps them stay on track with appointments and medications during treatment. It affects patients across every stage, from stage 1 colorectal cancer treatment through advanced disease. Financial stress can make it harder to keep up with cancer treatments and follow-up care, as some people may delay treatment or skip prescriptions due to cost concerns.
Beyond finances, the practical gaps are equally real. Transportation to weekly infusions, childcare coverage during appointments, and completing Family and Medical Leave Act (FMLA) paperwork are non-medical needs that can quietly destabilize even the most organized household. A social worker embedded in your care team, or one connected through your treatment facility, can help coordinate these logistics before they become crises.
Speaking with the hospital billing department before cancer treatment begins can unlock payment plans, charity care programs, and cost estimates. Many patients don’t realize this conversation is available to them. Pharmaceutical company patient assistance programs often cover co-pays or even full drug costs for qualifying patients, while government grants through agencies like the Health Resources and Services Administration (HRSA) may offer various types of support, though application processes can sometimes involve longer timelines. Ask your care team or a financial counselor whether these programs might be a fit for your situation.
Peer support matters too. Patients navigating treatment and beyond consistently report that connecting with someone who’s been through a similar diagnosis helps them manage the emotional challenges of isolation and fear. Building this layer of support early, before the hardest treatment weeks arrive, can help you navigate the mental hurdles you come across.
The emotional challenges don’t end when treatment does. When cancer treatment ends, you may experience complicated emotions including hope, worry, and fear. You might feel alone and lost without the regular support of your cancer care team, so it’s important to seek out emotional support from friends, family, support groups, or counselors during this transition. With that foundation in place, the next decision, how you fuel and care for your body during treatment, deserves equal attention.
Decision 5: Implementing supportive care
Supportive care is a clinical layer that runs parallel to treatment and directly affects how well your body tolerates every phase of your personalized care plan.
Palliative care deserves particular clarity here. Introduced early in the colorectal cancer diagnosis next steps process, palliative care focuses on symptom management, pain, fatigue, and nausea. Requesting a palliative care consultation at diagnosis, not later, is a structural decision your care team can facilitate today. With that physical foundation in place, what you eat and how you fuel recovery becomes the next practical focus.
What you need to know: key takeaways
When you’re newly diagnosed with colorectal cancer, the five decisions in this guide are your clearest path from overwhelm to agency. Whether you’re newly diagnosed with rectal cancer or colon cancer, the same structural logic applies: act deliberately, one decision at a time.
Here’s what to carry forward:
- Action over anxiety. Focus on your next concrete step, assembling your care team or staging your diagnosis, rather than projecting years ahead.
- Your care team is your most consequential choice. Prioritize multidisciplinary facilities, and don’t hesitate to seek a second opinion. It’s a clinical standard, not a sign of distrust.
- Biomarker and genetic testing can help guide your treatment decisions and are often recommended as part of your colorectal cancer care plan.
- Financial and emotional support are clinical necessities. Skipping them puts your ability to complete treatment at risk.
You don’t have to navigate this alone.
Disclaimer: The information provided in this article is for informational purposes only and is not intended to be a substitute for professional medical advice, diagnosis, or treatment. Outcomes4Me is not acting as your caregiver, and any suggestions or guidance offered should not replace the advice of your healthcare provider or qualified medical professional. Always seek the guidance of your physician or other qualified health provider with any questions you may have regarding a medical condition.
Personalized support for real care decisions
Understand your diagnosis, explore clinical trials, and track symptoms--all in one place.
Get started
Compare treatments, prepare for appointments, and track side effects—all in the app
Built for your diagnosis, Outcomes4Me gives you the tools to make confident, informed decisions—right when you need them.
Continue in app