

A uterine cancer diagnosis stops everything — and it’s completely understandable if your first instinct is to search for answers about what comes next. Understanding uterine cancer stages and prognosis is one of the most important steps you can take toward feeling informed and in control of your care.
You may have seen the terms “uterine cancer” and “endometrial cancer” used interchangeably. That’s because, as the Cleveland Clinic notes, uterine cancer most often starts in the endometrium — the lining of the uterus — making endometrial cancer the most common form. While other types of uterine cancer exist, endometrial cancer accounts for the overwhelming majority of diagnoses.
Your stage is a clinical tool, not a final verdict. Staging helps your care team understand where the cancer is and how it’s behaving — it shapes treatment decisions, but it doesn’t define your outcome. Prognosis depends on far more than a number, including tumor biology, your overall health, and the treatments available to you. Understanding what your tumor’s molecular profile can reveal adds another layer of context that staging alone can’t capture.
The goal here is clinical literacy — helping you ask sharper questions, have more confident conversations with your care team, and move through this process as an active participant in your own care. The next step is understanding exactly how staging works, starting with the system oncologists use most.
The FIGO system: decoding stages I through IV
Uterine cancer staging follows a single global standard — the FIGO (International Federation of Gynecology and Obstetrics) framework — giving every oncologist and patient a shared language for describing how far the disease has spread.
Understanding where your cancer falls within this framework directly shapes treatment decisions and helps contextualize endometrial cancer survival rates you’ll encounter in conversations with your care team. Here’s what each stage actually means:
- Stage I: The cancer is confined entirely to the uterus. It hasn’t moved into surrounding tissue, which generally makes it the most treatable category.
- Stage II: The cancer has spread into the connective tissue of the cervix (the cervical stroma), but according to Memorial Sloan Kettering Cancer Center, it has not extended beyond the uterus itself.
- Stage III: The disease has reached nearby structures — including the ovaries, vagina, or regional lymph nodes — signaling local or regional spread.
- Stage IV: This is the most advanced stage, where cancer has traveled to distant sites such as the bladder, bowel, or lungs.
Your stage tells you where the cancer is — but it doesn’t tell the whole story. Two patients with the same Stage III diagnosis can face very different outlooks depending on factors that go beyond anatomical spread. As Cancer Treatment Centers of America notes, staging is one critical input among several. The next layer of that picture involves how aggressive the tumor cells actually look — and that’s where grade and biomarkers come in.
Evidence-based guidance powered by NCCN Guidelines®
Personalized treatment plans shaped by the latest oncology standards—tailored to your diagnosis.
Get started
View your personalized treatment plan in the Outcomes4Me app
Use your diagnosis to unlock personalized NCCN Guidelines®-aligned recommendations.
Continue in app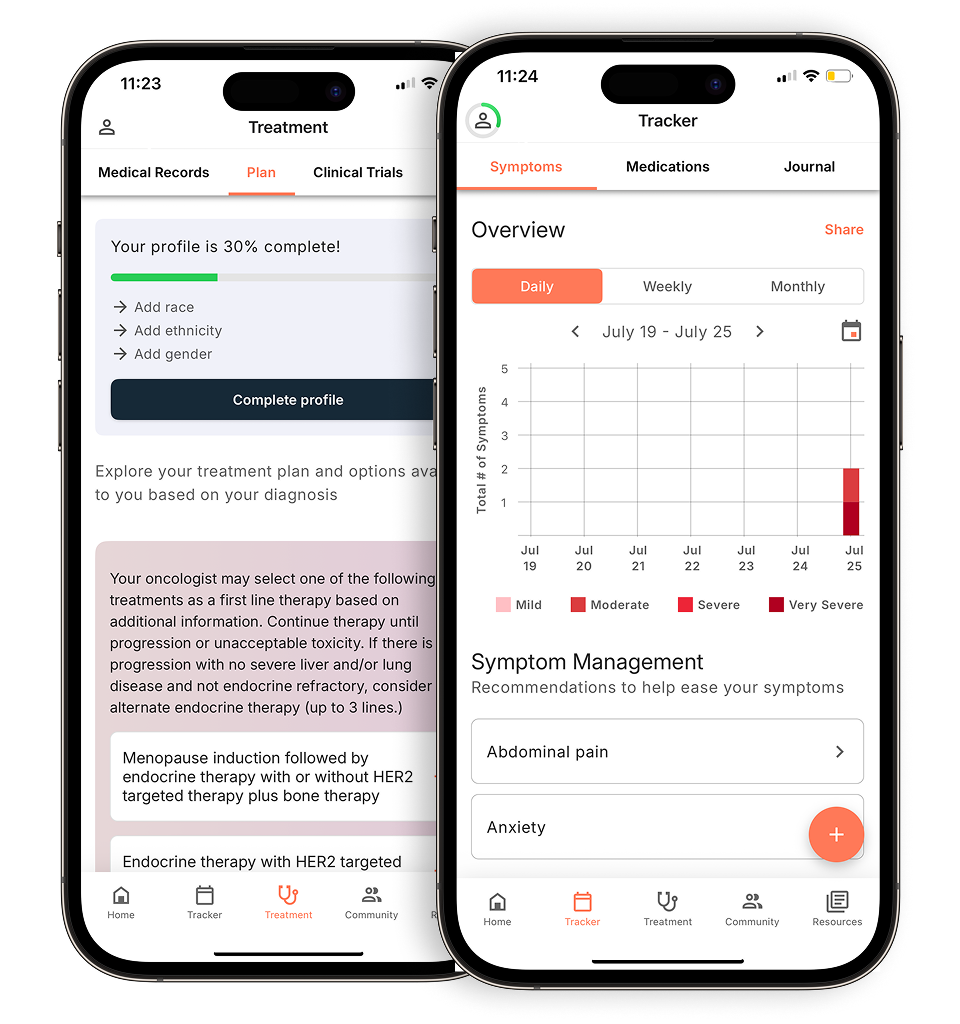
Why tumor grade and biomarkers redefine your outlook
Stage alone doesn’t tell your care team the full story — tumor grade and molecular markers are equally critical factors in understanding your prognosis and treatment options.
Grade describes how aggressive cancer cells look under a microscope. A Grade 1 tumor means the cells appear relatively normal and tend to grow slowly. Grade 3 cells look markedly abnormal and behave more aggressively. Grade 2 sits in between. This distinction carries real weight: according to Cure Today, tumor grade is a critical factor in prognosis, particularly for uterine cancer Stage II prognosis, where grade directly influences the risk of recurrence and shapes decisions about additional treatment after surgery.
Cell type adds another layer. Endometrioid tumors — the most common type — are generally slower-growing and caught early. Serous tumors, by contrast, are far more aggressive, more likely to spread, and typically assigned a higher-risk treatment plan regardless of stage at diagnosis. Understanding types of uterine cancer can help clarify what these distinctions mean for your specific situation.
Beyond grade and cell type, molecular biomarkers are increasingly shaping treatment decisions. Mismatch Repair (MMR) and Microsatellite Instability (MSI) testing can reveal whether a tumor has specific genetic instability patterns. MSI-high or MMR-deficient tumors may respond exceptionally well to immunotherapy — a treatment path that wouldn’t otherwise be considered based on stage alone.
Understanding these variables sets the stage for interpreting what survival statistics actually mean for your specific situation — which is exactly what we’ll explore next.
Understanding survival rates: data vs. reality
Survival statistics for uterine cancer offer genuine hope — but only when you understand what they actually measure. The SEER database tracks 5-year relative survival rates by stage, comparing how patients fare against the general population of similar age. Here’s what that looks like in practice:
- Localized (Stage I-II): approximately 95% 5-year relative survival rate — the foundation of a strong early stage uterine cancer prognosis
- Regional (Stage III): cancer has spread to nearby structures; survival rates drop meaningfully, though treatment advances continue to improve outcomes
- Distant (Stage IV): approximately 18% 5-year relative survival rate, according to SEER data via the American Cancer Society
“Relative” is the critical word here. These figures don’t reflect your individual probability — they compare a group of patients to the broader population, accounting for age and other health factors.
One important caveat that often gets overlooked: these statistics are built from patients diagnosed five or more years ago. That means they don’t yet capture the impact of newer immunotherapies, targeted agents, or the expanded role of biomarker-driven treatment decisions — topics covered earlier in this article. The landscape is shifting faster than the data can reflect.
Cancer care guidance for every step of your journey
Get treatment options, clinical trials, and support tailored to your diagnosis--all in one place.
Get started
See treatment options, manage symptoms, and stay informed—all in the app
View treatment options and trials personalized to your diagnosis—plus track progress in real time.
Continue in appThat gap between historical statistics and today’s treatment options is exactly why understanding what’s available right now matters so much — including options you may not have been offered yet. Both brachytherapy and immunotherapy are important treatment options that oncologists use for recurrent endometrial cancer, and awareness of these approaches can help you ask more targeted questions at your next appointment.
The role of clinical trials in modern uterine cancer care
Clinical trials aren’t a last resort — they’re increasingly a first-line consideration, and your staging conversation is the right moment to ask about them.
One of the most persistent myths in cancer care is that trials are reserved for patients who’ve exhausted every standard option. In reality, clinical trials are often the only way to access the latest advancements in uterine cancer immunotherapy. That distinction matters enormously, especially now that the treatment landscape is shifting so quickly toward targeted and immune-based therapies.
Staging opens the door to trial eligibility. Once your care team assigns a stage using the FIGO staging system and confirms your biomarker profile — as covered earlier — that same data determines which trials you may qualify for. NCCN guidelines now frequently list clinical trial participation as a preferred option alongside standard treatment, not a fallback. That’s a meaningful shift in how the oncology community thinks about personalized care.
The practical takeaway: ask your provider about trial eligibility at the staging appointment itself, not months later. Waiting can close doors. Early-stage patients especially may qualify for trials testing novel immunotherapies or combination regimens that aren’t yet available outside a research setting. Understanding how biomarker status shapes treatment access reinforces why this conversation belongs at the very start of your care plan — not at the end.
Pulling all of this together — your stage, grade, biomarkers, and trial options — forms a picture that’s far more actionable than any single data point alone.
The bottom line: 4 things to know about your diagnosis
Your stage is the map, but grade and biomarkers are the true engine of your prognosis — and understanding both transforms how you approach uterine cancer treatments.
Stage alone doesn’t tell the full story. A Stage I diagnosis and a Stage III diagnosis can each unfold very differently depending on tumor grade, histologic subtype, and biomarker profile. These factors determine not just your risk of recurrence, but which therapies are most likely to work for you.
Here are the four things worth holding onto as you move forward:
- Early detection matters enormously. Stage I uterine cancer carries a survival rate of approximately 95%, which is why prompt evaluation of symptoms — and swift treatment — is so critical.
- Grade and biomarkers drive treatment decisions. Tumor grade tells your care team how aggressively the cancer may behave. Biomarker results, particularly MSI/MMR status, determine whether you’re eligible for immunotherapy and other targeted options. Learning how to interpret your pathology results early puts you in a stronger position during treatment conversations.
- Biomarker testing is standard of care, not optional. Every patient should expect MSI/MMR testing as part of their workup — full stop.
- Personalized tools can close the knowledge gap. NCCN guidelines are the gold standard for oncology treatment recommendations, but navigating them without support is overwhelming. Digital platforms that integrate your biomarker results with NCCN guidance and clinical trial matching can help you understand your options clearly.
Knowing these four pillars sets you up to do more than receive a treatment plan — it prepares you to actively shape one. The next step is knowing exactly how to do that.
Taking control: How to navigate your treatment path
Your uterine cancer diagnosis is the starting point — not the whole story — and understanding that distinction puts you in the driver’s seat of your own care.
The sections above make one thing clear: stage alone doesn’t define your prognosis or your options. Grade, histology, and biomarker testing for uterine cancer are equally critical pieces of the picture. The more fluent you become in your own diagnosis, the more effectively you can advocate for personalized care.
That’s where Outcomes4Me comes in. As the only direct-to-patient platform that integrates with NCCN® treatment guidelines, Outcomes4Me helps you connect your genetic results, biomarker findings, and staging information to evidence-based treatment options and clinical trials — all in one place. You don’t have to piece this together alone.
Before your next appointment, bring these three questions to your oncologist:
- “What is my tumor grade and histologic subtype?” Understanding whether you have endometrioid or a high-risk subtype like serous or clear cell shapes everything from treatment intensity to follow-up frequency.
- “Has my tumor been tested for MSI/MMR status and POLE mutations?” These results can determine eligibility for immunotherapy and may significantly affect your prognosis.
- “Am I a candidate for any clinical trials based on my biomarkers?” Targeted therapies tied to specific mutations are one of the fastest-evolving areas in uterine cancer care.
The landscape of uterine cancer treatment is advancing quickly, and you deserve to benefit from every option available to you. With the right information and the right tools, navigating your path forward is possible — and you don’t have to do it alone.
Personalized support for real care decisions
Understand your diagnosis, explore clinical trials, and track symptoms--all in one place.
Get started
Compare treatments, prepare for appointments, and track side effects—all in the app
Built for your diagnosis, Outcomes4Me gives you the tools to make confident, informed decisions—right when you need them.
Continue in app




